Many medical practice owners can’t tell you what a new patient costs them. They know what the marketing bill is. They know roughly how many new patients showed up last quarter. They don’t connect the two — and without that connection, every marketing decision is a guess. The Google Ads campaign that “feels productive” might be losing money. The referral source that quietly produces three patients a month might be the most profitable channel in the practice.
This post walks through how to calculate patient acquisition cost (PAC) and patient lifetime value (LTV), the ratio that decides whether a practice is profitable on growth, and where the biggest leverage points sit. There’s an interactive calculator at the end you can use with your own numbers.
The two numbers that drive everything
Patient Acquisition Cost (PAC)
PAC is the all-in cost to convert a stranger into a paying patient. The basic formula is straightforward: total marketing and sales spend in a period, divided by the number of new patients acquired in that period.
“All-in” matters. Most practice owners count the Google Ads invoice and stop. The real number includes: ad spend across all channels, the website costs (build, hosting, ongoing maintenance), the SEO retainer, content and design work, any referral incentives or community outreach budget, and a portion of front-desk staff time that’s spent on intake. Skip any of those and your PAC looks artificially good.
The ranges are wide by specialty, but published industry benchmarks give a sense of scale. Primary care typically runs $200–$250 per new patient, dental around $300, specialties like orthopedics and cardiology in the $350–$450 range. Specialty practices with high-value procedures can sustain PAC of $1,000–$3,000+ because procedures generate proportionally higher revenue. Cosmetic, fertility, and aesthetic practices can absorb even higher PAC because of premium pricing.
Patient Lifetime Value (LTV)
LTV is the total revenue a single patient generates from first visit to last. The simplest version of the formula is: average revenue per visit × visits per year × years the relationship lasts.
Industry data suggests revenue per visit varies dramatically by specialty — about $279 for the average dermatology visit, around $627 for the average orthopedic visit. A patient who comes in once a year for ten years is fundamentally different economics from a patient who comes in twelve times in a single treatment cycle and never returns.
The mistake most practices make is using the gross revenue number. You want to subtract overhead — staff, supplies, malpractice insurance, rent — to get a contribution-margin LTV. Two practices with the same gross revenue per visit can have wildly different lasting LTV depending on overhead. The contribution-margin number is what should be compared to PAC.
The ratio that decides profitability
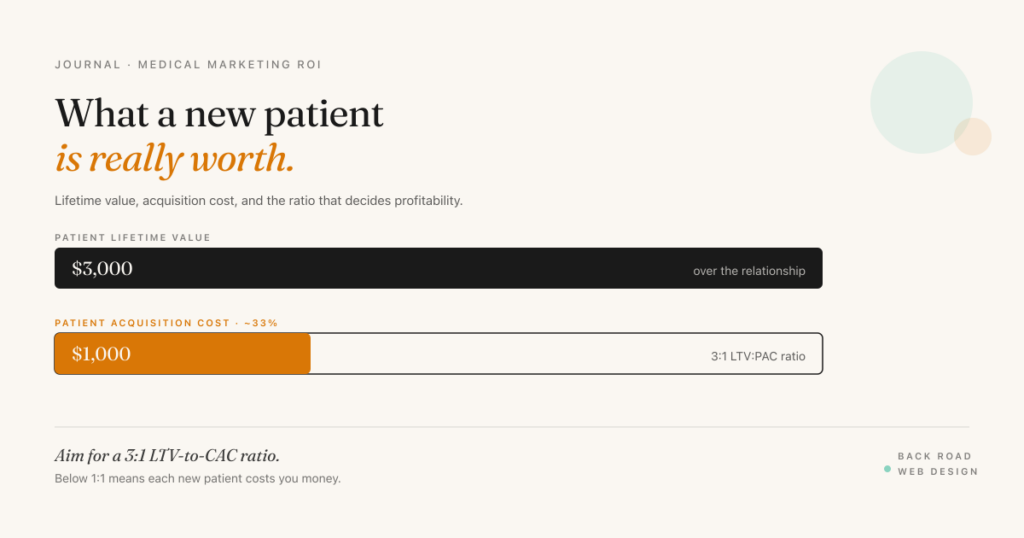
The standard healthcare benchmark is a 3:1 LTV-to-PAC ratio. A ratio below 1:1 means you’re spending more to acquire a patient than the patient will ever generate in net revenue — every new patient is a loss. A 1:1 ratio means break-even on growth. A 3:1 ratio is what well-run practices target.
Why 3:1 specifically? Because the gross LTV number ignores the cost of clinical delivery — the staff time, supplies, and overhead it takes to actually treat the patient. A 3:1 ratio leaves enough margin after acquisition cost and clinical cost for the practice to be genuinely profitable. Specialty practices with high-margin procedures can sometimes thrive at 2:1 because their per-visit margin is higher. Primary care practices often need ratios closer to 4:1 because per-visit margin is thinner.
Calculate your practice’s numbers
Plug in your real figures. The calculator works it through and shows you the ratio with context.
PAC + LTV CALCULATOR
Calculate your ratio.
Strong margin — you have room to grow acquisition spend or invest in patient retention to push LTV higher.
Where the leverage lives
If your ratio is too low, there are exactly four levers to pull. In rough order of leverage:
1. Track which channels produce patients
Most practices look at PAC as a blended number across all marketing. The blended number hides massive variation. Channel-specific PAC analysis often reveals dramatic gaps — paid search at $1,400 per patient versus referral programs at $280, hidden under a blended average. A practice spending $4,000 a month split equally across Google Ads, Meta, and a local sponsorship might be acquiring 80% of its new patients from one channel and wasting two-thirds of the budget on the other two.
The fix is intake tracking. When new patients call or book online, ask "how did you hear about us" and log the answer in the practice management system. Tag every form submission with its source via UTM parameters. Six weeks of disciplined tracking is enough to see the channel breakdown clearly.
2. Improve retention before scaling acquisition
If your LTV is being held down by low retention — patients who come once and don't come back — pumping more money into acquisition is throwing good money after bad. The cheapest patient is the one you already have. Recall systems, post-visit follow-up, transparent treatment plans, and accessible scheduling all extend the relationship. A two-year average becoming a four-year average doubles LTV without changing acquisition spend at all.
3. Tighten the ad spend on the channels that work
Once you can see PAC by channel, you can reallocate. Cut the weakest channel entirely. Reinvest in the strongest. The same total budget producing the same patient count means lower PAC and higher ratio — a structural improvement, not a one-time bump.
4. Add a referral program with measurable economics
Referrals are the cheapest acquisition channel almost universally. The mistake most practices make is treating referrals as something that just happens. They don't — they happen when patients are reminded to refer and given an easy way to do it. Even a modest referral incentive (a small gift, a discount on a non-covered service) plus a system that prompts the ask after a positive visit can produce a meaningful share of new patients at a PAC close to zero.
How to read your number
If your ratio is below 1:1, the practice is hemorrhaging money on growth — every new patient is a loss after overhead. This needs immediate attention before any other marketing decision.
If your ratio is between 1:1 and 2:1, you're in break-even territory. You're paying for the marketing with the patients it produces, but you're not actually growing the practice's profitability. The two highest-leverage moves are channel-level PAC tracking and retention improvements.
If your ratio is between 2:1 and 3:1, you're profitable on growth. Specialty practices with high per-visit margin can stay here comfortably. Primary care should push higher.
If your ratio is above 3:1, you're well-run on growth economics — and you might be under-investing in marketing. The instinct is to keep spend low because the ratio looks great, but a 5:1 ratio means you're leaving growth on the table. Spending more — and accepting a lower ratio in exchange for substantially more patients — often produces more total profit.
Want help running these numbers for your practice?
I'll review your last 6 months of marketing spend, attribution, and patient retention data — then send you a written report showing your real PAC by channel, your lasting LTV, and the specific moves with the biggest leverage on your ratio.
Get a free practice marketing audit →